
How to Negotiate Better Payer Contracts: A Guide for Independent Practices

Negotiating a payer contract starts with a specific question: which reimbursement changes would make a meaningful difference to your practice, and what evidence supports them?
For an independent outpatient practice, a useful preparation process is to review your current fee schedule, identify high-impact services, compare appropriate local peers, and turn those findings into a focused request. A benchmark can help you choose where to concentrate your effort. It cannot guarantee that a payer will agree to your proposed rates.
This guide walks through that process, from organizing your data to checking that an accepted rate change reaches your claims.
Before the five-step workflow: confirm the contract
Start with the agreement and fee schedule that actually apply to your practice. Record the payer, product or network, contracting entity, effective dates, and any notice provisions that affect when you can request a review.
A payer’s brand name alone may not identify the relevant contract. Different products, networks or group arrangements can have different rates. If you bill through an IPA, CIN or other organization, clarify which agreement governs your reimbursement before comparing it with a direct contract.
Keep two questions separate:
- Is the payer paying the agreed rate? A payment below your applicable contract may require a claims or payment review.
- Is the agreed rate competitive? A contract that is paid correctly may still compare poorly with relevant local benchmarks. That is a rate-negotiation question.
This distinction helps you bring the right problem to the right payer contact. Before changing participation or sending a termination notice, review the agreement with a qualified adviser; a rate comparison alone is not enough to make that decision.
Payer contract negotiation checklist
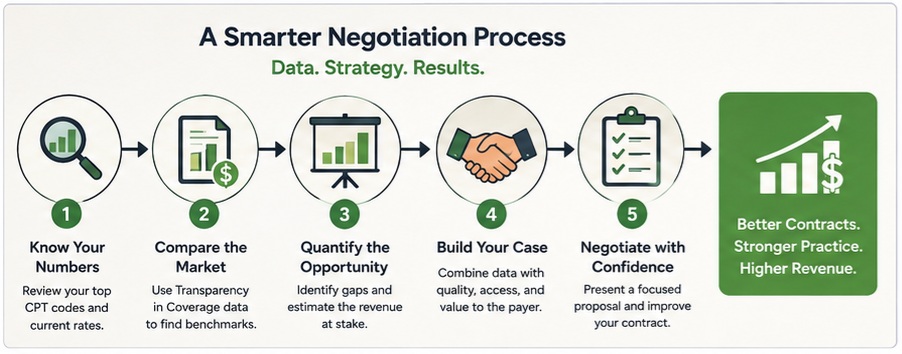
- Know your numbers: Review priority CPT/HCPCS codes, current rates, volume and revenue exposure.
- Compare the market: Use relevant Transparency in Coverage data to find appropriate peer benchmarks.
- Quantify the opportunity: Identify meaningful gaps and model the revenue at stake.
- Build your case: Combine the rate evidence with supportable information about quality, access and network value.
- Negotiate with confidence: Present a focused proposal, evaluate the response and verify implementation.
1. Know your numbers
Use your billing or practice-management records to build a short list of important services for the payer you are reviewing. Include CPT/HCPCS codes, relevant modifiers, place of service, annual units, and the current contracted rate or a carefully reconciled allowed amount.
Keep billed charges, allowed amounts, insurer payments and patient responsibility distinct. Comparing a peer’s negotiated rate with only the insurer-paid portion of one of your claims can create a misleading gap.
Prioritize codes with meaningful volume or revenue exposure. A large percentage difference on a rarely billed code may matter less than a smaller difference on a service you perform every day. Note unusual claims, denials or payment rules separately rather than allowing them to distort your baseline.
The result should be a manageable payer-specific worksheet, not every code your practice has ever billed.
2. Compare the market
Transparency in Coverage files provide a source of published negotiated-rate information. CMS describes public in-network rate files and out-of-network allowed-amount files as separate disclosures. For commercial contract benchmarking, the relevant starting point is usually the in-network rate data. CMS: Plans and Issuers
Public availability does not make every number a useful comparison. Before relying on a benchmark, check:
- Payer and plan: Does the published rate correspond to the product or network you are evaluating?
- Code and payment basis: Are the code, modifiers, units and rate type comparable? A percentage-based entry should not be interpreted as a dollar amount.
- Setting: Are you comparing professional office services with professional office services, rather than mixing facility and professional reimbursement?
- Peers: Do the specialty, geography and organizational characteristics make sense for your practice?
- Provider identity: Is the rate associated with the correct billing organization or provider relationship?
- Source quality: Are dates, duplicate entries, implausible values and missing data accounted for?
Look at the distribution of relevant rates, not only the highest number. A large group’s rate or an unusual published entry may not be a realistic target for your practice. Conversely, a statewide average can obscure important local differences.
Published rates are benchmarking inputs, not proof of what a particular claim will pay. Missing data does not prove a provider is out of network. Shared published rates do not, by themselves, establish a contractual affiliation between organizations.
For more background, see how Transparency in Coverage data becomes a reimbursement benchmark.
3. Quantify the opportunity
Choose a proposed rate or range for each priority code using the available peer evidence, your practice’s circumstances and the strength of the comparison. Document why you selected that target and where the data is limited.
Then calculate a planning scenario:
Proposed rate change per unit × expected annual units for that payer = modeled annual change in allowed revenue.
Example: What Rate Variation Looks Like in a Real Local Market
The reason payer contract negotiation matters is simple: practices doing similar work in the same market are not always paid the same.
The following example uses output from Reveon Health’s analysis workflow.
A small internal medicine practice in the Atlanta area wants to understand whether its UnitedHealthcare reimbursement is competitive. The practice wants to compare itself against other internal medicine providers and small provider groups in the area.
Using Reveon Health, the practice filters the market by:
- Specialty: Internal Medicine
- Payer: UnitedHealthcare
- Provider group size: 1 to 9 providers
- Service: a selected high-volume internal medicine CPT code, 99213
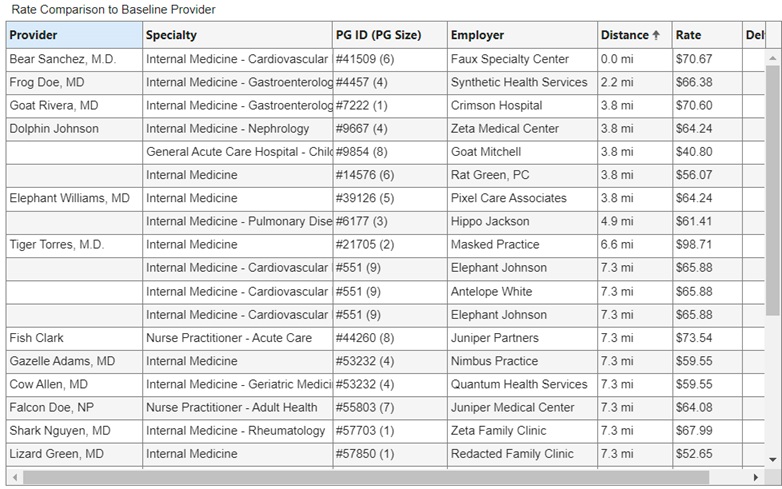
The result is immediately useful.
Some Quick Math
Among nearby small internal medicine groups, the visible rates for the same payer and same selected service vary widely. In this simple local comparison, rates range from approximately $40.80 to $98.71.
That is not a small difference.
A practice being paid around $70.67 for 99213 might feel like its reimbursement is reasonable until it sees another comparable local group being paid $98.71 for the same type of service. That is a difference of about $28 per visit, or roughly 40% higher than the practice’s current rate.
Now translate that into practice economics.
If that CPT code is billed 1,000 times per year for UHC, a $28 improvement would represent approximately:
1,000 visits × $28 = $28,000 in modeled annual opportunity
And that is just one CPT code. For a single payer.
Most practices do not have only one important service or one commercial payer. They have a set of high-volume codes that drive the majority of their commercial revenue. If several of those codes are 10%, 15%, or 20% below local benchmarks, the total opportunity can become meaningful very quickly.
This is exactly why generic payer negotiation advice is not enough.
A practice owner does not need to know that “rates vary.” They need to know specific regional market rates for peer specialties on high volume codes that matter, so that they can get a feel for how much revenue may be at stake during renegotiation.
With that information, the conversation changes into a credible negotiation position.
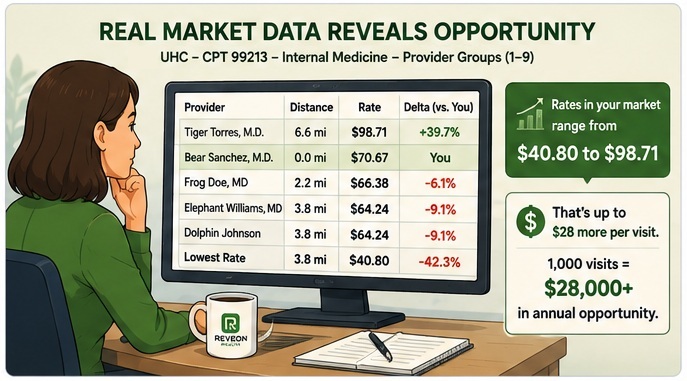
This Reveon product-output example shows a published benchmark opportunity based on the displayed rates and an assumed 1,000 annual units. It does not represent guaranteed collections, a guaranteed negotiated rate increase, or a verified client outcome.
The estimate assumes the new rate applies to those units and that volume remains unchanged. Collections may differ because of patient responsibility, denials, benefit rules and other factors. If the new schedule takes effect partway through the year, model the first year separately.
Evaluate the full proposed schedule as well. An increase on one code can be offset by lower rates or less favorable terms elsewhere. Medicare comparisons can provide context, but they should not replace a relevant commercial-market comparison.
4. Build your case
Make it easy for the payer representative to understand what you want reviewed. A practical submission includes:
- Your practice and the contract or product being discussed.
- A short list of requested code-level changes.
- Your current rates and proposed rates.
- A summary of the benchmark methodology and its limitations.
- Documented reasons your practice matters to the network, such as access or service availability.
- A request for the appropriate review process and next step.
Use only quality, access or cost claims you can support. Do not imply that your practice reduces spending or improves outcomes without evidence.
For example, the opening of a request might read:
“We would like to request a fee-schedule review for our practice’s participation in [product/network]. We have identified several frequently billed services where our current rates compare below the selected local peer benchmarks. The attached summary identifies the codes, current rates, proposed adjustments and comparison method. Could you confirm the appropriate contact and process for reviewing this request?”
This is a starting template, not a substitute for the terms of your agreement. Keep detailed supporting material available, but lead with a clear request rather than an unexplained spreadsheet.
If you need help preparing the benchmark evidence, Reveon’s Contract Rate Benchmark Report provides done-for-you analysis for an existing practice considering renegotiation. It starts at $595 for one payer. The report supports your negotiation preparation; it does not promise a payer concession or replace legal review.
5. Negotiate with confidence
Submit the focused proposal and ask for the appropriate contracting contact, review process and next step.
Follow through: evaluate the offer and verify implementation
If the payer responds with a counteroffer, apply the proposed schedule to your own service mix. Compare the modeled result with your starting point and your original request. Do not judge an offer solely by its headline percentage increase.
Clarify which providers, products, codes and dates the change covers. Check whether the proposal affects other contract terms. Keep a written record of what was agreed and the applicable effective date.
After implementation, review a sample of eligible claims against the updated schedule. If the expected rate is not appearing, investigate the applicable product, coding and implementation details before assuming the negotiation failed.
If the payer declines, ask what evidence or circumstances could support a later review. Reassess the opportunity alongside your other contracts rather than escalating on the strength of one comparison alone.
Common questions about negotiating payer contracts
Can a small practice request better reimbursement rates?
A practice can ask for a review, but the outcome depends on the agreement, payer process, network circumstances and the evidence supporting the request. Start with a focused proposal and the correct contracting contact.
What percentage increase should we request?
There is no universal percentage that fits every practice. Select targets from relevant comparisons and model them against your actual service mix. A headline increase can conceal very different effects across codes.
Does a below-market rate mean the payer underpaid our claims?
No. A payer may be paying your current contract correctly even when that rate is below a selected market benchmark. Contract compliance and market competitiveness are different analyses.
Do we need software to prepare a negotiation?
Not necessarily. If your immediate need is evidence for a particular contract review, a done-for-you report may be more practical than learning an analytics platform. Ongoing software access is a separate option for people who need to run repeated analyses.
What if we are opening a new practice?
Without an existing schedule or claim history, the question is how to evaluate the market and proposed payer terms. Reveon’s New Practice Market-Entry Report addresses that different starting point and starts at $495 for one payer.
Choose the right next step for your practice
Ready to prepare a payer-specific case? Explore the Contract Rate Benchmark Report.
Only need a focused comparison with named competitors? The $150 Competitor Rate Snapshot has a narrower scope and is not a full negotiation report.
Unsure whether usable data is available for your practice and market? Request a Free Rate Opportunity Screen to check data coverage and fit for further analysis. The screen is not a full benchmark report or a payer-ready negotiation package.
See Clearly. Negotiate Smarter.